
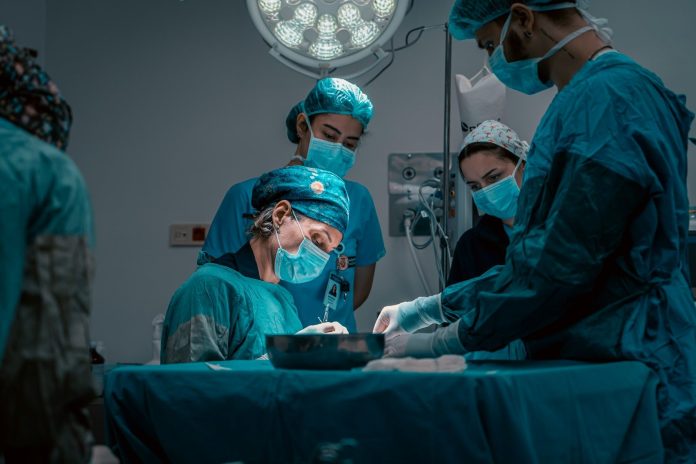
Ask most people why surgeons burn out and they’ll point to the hours and the pressure. The bigger culprit is physical. Surgeons hold awkward, near-frozen postures for hours at a stretch, and the body sends the bill later, in the form of neck pain, shoulder injuries, spine problems, and early retirements the specialty can’t afford.
The research isn’t subtle. A widely cited review of surgeon musculoskeletal health reports that more than 80% of surgeons experience a work-related injury or illness over the course of a career, largely from holding awkward or static positions during long operations.
That isn’t a wellness issue. It’s a workforce issue, and it’s already shaping who stays in the OR, who leaves, and how patients fare on the table.
The Injury Rate Is a Practice-Management Problem
Surgeon injuries don’t stay with the surgeon. When a senior operator cuts back on cases, refers out complex procedures, or retires five years earlier than planned, the hospital loses volume, trainees lose a teacher, and patients lose access to someone at the peak of their judgment.
The interventions that hold up under study are the ones that change the physics of the case, starting with table-mounted retractor systems that take the work of holding exposure off human arms and transfer it to a rigid frame anchored to the bed, stabilizing the field and letting the surgeon stand in a neutral posture.
Orthopedic surgery has been studied most closely, and the numbers there are hard to shrug off. A recent review found that musculoskeletal injuries affect at least four in ten orthopedic surgeons, and roughly one in three of those injured surgeons ends up taking leave, modifying their practice, or retiring earlier than planned. Female surgeons often report higher rates of discomfort and injury tied to instrument design that was never sized for their hands.
Why the Obvious Fixes Don’t Work
The intuitive response is to tell surgeons to stand up straighter, stretch between cases, and take microbreaks. All of that helps at the margins, but none of it addresses the room.
Operating rooms were built around the patient and the equipment, not the person holding the instrument. Consider what a surgeon actually contends with:
- Fixed table heights. Tables adjust, but rarely enough for a team of mixed heights working the same field. Someone usually ends up craning or hunching.
- Monitors placed for the room. Screens in laparoscopic and robotic cases often sit where they fit, not where the neck wants them, forcing hours of rotation and tilt.
- Instruments sized for the average hand. Grip spans and trigger forces punish smaller hands and repetitive pinch grips over long cases.
- Hard floors and lead aprons. Standing on concrete under twenty pounds of shielding is its own occupational exposure.
Wellness posters and yoga blocks can’t undo eight hours of that. The load has to come off the surgeon before the shift ends, not after it.
What Actually Moves the Needle
Better exposure tends to mean shorter cases, and shorter cases mean less cumulative loading on every person in the room. Beyond retraction, the American College of Surgeons has published best-practice recommendations that treat ergonomics as a technique to be taught, not a personality trait. Adjusting table height for the primary surgeon, putting monitors at eye level and directly ahead, taking short intraoperative stretch pauses on long cases, and rotating tasks among the team all show measurable benefit.
Patients Have a Stake in This Too
A fatigued surgeon is a less precise surgeon. Tremor increases, decisions slow, and the last hour of a long case doesn’t look like the first. Every step that reduces static loading, whether it’s better retraction, better sightlines, or better instrument fit, buys back some of that precision for the patient on the table.
The specialty is short on surgeons and getting shorter. Keeping the ones already trained healthy enough to operate into their sixties isn’t a perk. It’s a supply problem with a physical solution, and the solutions have been sitting in plain sight for a while now.







